
Medtransic Logo

Applied Behavior Analysis Billing

ABA Billing Services for Agencies and BCBA-Owned Clinics

Medtransic bills insurance and handles credentialing for ABA agencies and BCBA-owned clinics. We track every authorization by client, payer, hours and dates, and bill the work of BCBAs, assistant behavior analysts and RBTs to each payer's rules, inside CentralReach or the system you already use. Billing is 4-8% of what we collect for you. Credentialing is $150 per application, per provider. There is no long-term contract.

Your authorization is the budget. It empties daily, and hours past it go unpaid.

ABA is under active federal audit. In a February 2026 review of Colorado's Medicaid ABA payments covering 2022 and 2023, every one of the 100 sampled enrollee-months contained at least one claim line that was improper or potentially improper, with missing or incomplete documentation the most common problem, in 93 of the 100 (HHS Office of Inspector General, report A-09-24-02004).

Every state mandates autism coverage, but self-funded plans are often exempt.

What an approved block of hours actually doesIllustrative sample
Approved block120 hours
DeliveredRemaining
Week 120 h100
Week 222 h78
Week 320 h58
Week 424 h34
Week 522 h12
Week 622 h-10
1 week delivered past the approval10 h

Nothing on a claim shows this balance. The practice usually learns the block was empty when the remittances come back short, by which point the technicians have already been paid for the work.

Where ABA Practices Actually Lose Money

ABA does not usually lose money the way other specialties do. The claims are not the problem; what happens before and around them is.

Care Delivered After the Authorized Hours Run Out Is Usually Care Nobody Pays For

A payer approves a block of hours for a set window, and that block drains a little every day the child is seen. When it empties mid-month, the sessions keep happening because the family and the team are mid-program. Those sessions are delivered, documented, and unpaid.

A State Mandate Does Not Mean the Family's Plan Actually Covers ABA

Every state requires autism coverage, so practices reasonably assume the benefit is there. Those mandates generally reach fully insured plans and not self-funded employer plans. Verifying which kind of plan a family holds, before the first session, is what separates a funded case from months of free care.

Supervision and Direct Therapy Billed As If They Were the Same Thing

An analyst supervising and a technician delivering therapy are different services with different rules, and sometimes they happen in the same room at the same time. Flattening them into one line is a reliable way to lose the supervision revenue entirely or to trigger a review of both.

Thin Progress Data Turns a Renewal Into a Reduction

Reauthorization is a clinical argument, and the plan is deciding whether the hours it already bought produced change. When the update restates the diagnosis instead of showing movement against the treatment plan, the renewal tends to come back with fewer hours than the child needs.

Daily Service Means Errors Compound Before Anyone Catches Them

Most specialties see a patient weekly or monthly. ABA can run several hours a day, five days a week, so a single misunderstanding about how sessions are recorded is not one bad claim. It is forty of them by the time the first remittance comes back.

Session Records That Do Not Match the Hours Claimed

ABA documentation is generated by technicians in the field, often on a phone, between sessions. When the recorded time and the claimed time drift apart, the payer's own audit finds it eventually, and the recovery comes out of money the practice already spent on payroll.

How We Protect the Hours You Are Owed

Each of these answers one of the failures above, in the same order.

Authorization Tracked as a Balance, Not a Filing

We treat an authorization the way a bank treats an account: a starting balance, a running total, and a warning well before it empties. The practice finds out that hours are running low while there is still time to request more.

Remaining authorized hours visible before they run out / Renewal requests started early rather than after the gap / Hours delivered outside an authorization flagged quickly / Every authorization tied to the client it belongs to

Benefits Checked Properly Before Intake

We confirm what the plan actually is and what it actually covers before the practice commits clinical capacity to a family, so the funding question is answered at intake instead of discovered in month three.

Plan type identified, including self-funded plans outside state mandates / Age limits, hour caps and diagnosis requirements confirmed up front / Any required diagnostic evaluation confirmed as covered before referral / Families told what they owe before treatment starts, not after

Supervision, Assessment and Direct Therapy Billed as Distinct Work

Analyst time, technician time and assessment time are separated and presented the way payers expect, so the practice is paid for the clinical oversight it is required to provide rather than absorbing it.

Supervision captured instead of quietly written off / Concurrent analyst and technician time handled to plan rules / Assessment and treatment planning billed as their own work / Parent and caregiver training claimed where the plan covers it

Reauthorization Supported With What Payers Actually Read

We work the renewal calendar with the clinical team so requests go in with current progress data attached, which is the difference between hours renewed and hours cut.

Renewal deadlines tracked per client, not per practice / Progress documentation assembled before the request goes out / Reductions appealed with data rather than accepted / Lapses between authorization periods kept rare

What We Handle for ABA Practices

From the first benefit check through to appealing a reduced renewal, handled as one job rather than four.

01

Authorization Management

Initial requests, ongoing balance tracking and renewals handled end to end, so the practice always knows how many approved hours are left for every client on the caseload.

Initial authorization requests submitted and chased / Running balance of approved hours per client / Early warning before a block is exhausted / Renewal requests filed ahead of the expiry date

02

Benefit and Plan Verification

Coverage confirmed before intake, including whether the plan is subject to the state autism mandate at all, plus any caps and conditions attached to the benefit.

Fully insured versus self-funded plan identification / Age, hour and setting limits confirmed / Diagnostic evaluation requirements checked / Patient responsibility calculated before the first session

03

Session and Supervision Billing

Daily technician sessions, analyst supervision, assessment and caregiver training all submitted as the distinct services they are, matched to the records that support them.

High-volume daily session billing / Analyst supervision captured and claimed / Assessment and treatment planning billed / Caregiver training claimed where covered

04

Denials, Appeals and Recovery

Denied and reduced ABA claims worked rather than written off, with particular attention to the authorization and documentation reasons that dominate this specialty.

Authorization-related denials appealed / Reduced hour awards challenged with progress data / Underpayments identified and pursued / Reporting on what is paid, pending and at risk

Inside ABA Billing

01

How to Choose an ABA Billing Company

The right ABA billing company is the one that treats the authorization as the budget. Ask every company you talk to the same six questions.

Six questions to ask

  1. 01How do you track authorized hours, and who tells us before a client runs out?
  2. 02How do you bill supervision, assessment and direct therapy so they are not mixed up?
  3. 03What do you need from our session notes, and who checks them against the hours claimed?
  4. 04What do you charge, what moves the rate, and is there a minimum or a long contract?
  5. 05How do we leave, and what happens to open claims if we do?
  6. 06Do you bill inside our system, what reports will we see, and is credentialing included?

Our answers

  • Authorizations are tracked as a balance against each client's approved hours.
  • Billing is 4-8% of collections. Basic billing is 4%; prior authorizations, more providers or more work move it up.
  • There is no long-term contract. You can leave with 60 days' notice, and we work your open claims in that time.
  • Access to client records is set by role.
  • We bill inside CentralReach or the system you already use, report what is paid, pending and at risk, and credential your BCBAs and other providers separately at $150 per application, per provider.

Ask how authorized hours are tracked before a client runs out

Ask how supervision and direct therapy are billed apart

Ask what moves the rate, and how you leave

Billing is 4-8% of collections; 60 days' notice to leave
02

The Authorization Is the Budget, and It Empties Every Day

In most specialties the claim is the unit of risk. In ABA the authorization is, because a payer does not approve a service, it approves an amount of service for a period of time.

A block of hours is granted, and it depletes with every session the team delivers. Nothing about that depletion is visible on a claim, which is the problem: the practice usually finds out the block is empty when remittances start coming back with nothing on them.

By then the hours are spent. The technicians were paid, the family was served, and the money is gone. Treating the authorization as a running balance rather than a document in a folder is what turns that from a recurring loss into a question the practice answers in advance.

Payers approve an amount of service for a window, not a service

The balance depletes daily and nothing on a claim shows it

Practices typically discover the gap after payroll is already spent

A tracked balance converts a surprise into a scheduled renewal

03

Why a State Mandate Is Not the Same as a Benefit

Every state has an autism insurance mandate. That fact is true, widely reported, and routinely misread by practices as meaning that any family walking in the door has ABA coverage.

Those mandates generally govern fully insured plans, the kind an insurer sells and bears the risk on. A large share of employer coverage is self-funded instead, where the employer pays the claims and the insurer only administers them, and self-funded plans generally sit outside state insurance mandates. The card in the family's wallet looks identical either way.

So the question that matters at intake is not which state you are in. It is which kind of plan this is, what it caps, and what it requires before it will pay. Answering that before the first session is the single highest-value administrative act in an ABA practice.

All states mandate autism coverage; mandates generally reach fully insured plans

Self-funded employer plans are typically outside those mandates

The insurance card looks the same for both kinds of plan

Plan type, caps and conditions belong in the intake conversation

04

Renewals Are Won With Progress, Not Paperwork

Reauthorization decides how much care a child gets for the next several months, and it is decided by someone reading whether the last block of hours accomplished anything.

That reader is looking for movement against the treatment plan: what was targeted, what changed, what the data shows. An update that restates the diagnosis and repeats the original goals answers none of that, and the result is often not a denial but a reduction, which is harder to notice and harder to appeal.

The practices that hold their hours are the ones where the renewal is assembled before the deadline, with current data attached, as a normal part of the clinical calendar. That is a scheduling problem as much as a clinical one, and it is solvable.

Renewals are judged on whether purchased hours produced change

A restated diagnosis is not progress data

A thin update often ends in a cut, not a denial

Cuts are quieter than denials and often go unappealed

05

Daily Service Turns Small Errors Into Large Ones

An ABA caseload does not behave like a weekly therapy caseload. A single child may be seen for several hours a day, most days of the week, by more than one technician.

That volume is what makes the specialty financially viable and it is also what makes it unforgiving. A misunderstanding about how session time should be recorded does not produce one questionable claim. It produces every claim for that client, that month, in the same wrong shape, and it is discovered after all of them have been submitted.

The fix is not more diligence from clinicians who are already stretched. It is catching the pattern on the first few claims, which requires somebody looking at ABA claims specifically rather than processing them alongside everything else.

Several sessions a day, multiple technicians, one client

One misunderstanding replicates across an entire month of claims

Errors surface only after the whole batch is submitted

Catching the pattern early beats asking clinicians to be more careful

What Each Funder Expects

ABA is funded through four quite different routes, and the administrative path matters as much as the clinical one. Treating them as interchangeable is where avoidable denials come from.

Commercial

Commercial Plans

  • Confirm whether the plan is fully insured or self-funded before intake - state autism mandates generally do not reach self-funded employer plans
  • Most plans require a diagnostic evaluation from a qualifying provider before ABA is authorized at all, and will not backdate approval to cover sessions already delivered
  • Authorizations are granted as a block of hours for a fixed period; track what remains rather than assuming the period is the limit
  • Caregiver training is covered by many plans but is frequently left unbilled because it does not look like a therapy session

Medicaid

Medicaid

  • Medicaid covers medically necessary ABA for eligible children through the federal early and periodic screening benefit, so a state plan that appears silent on ABA is not the same as no coverage
  • Provider qualification and supervision requirements are stricter and more explicitly enforced than on most commercial plans
  • Managed care organizations administering Medicaid set their own authorization and renewal processes, which vary within the same state
  • Reimbursement is generally lower, which makes unbilled supervision and lapsed authorizations proportionally more damaging

All payers

TRICARE and Military Families

  • ABA for military families runs through a dedicated autism program with its own enrollment and provider requirements, separate from ordinary medical benefits
  • Families relocate often, so coverage continuity and provider enrollment in the new region need handling before the move, not after
  • Required assessments and outcome measures sit on a set schedule and missing one can interrupt authorization
  • The administrative path differs enough from commercial billing that treating it as just another payer produces avoidable denials

All payers

School and Regional Programs

  • Services funded through a school or a state developmental program follow that program's rules and are generally not billed to health insurance
  • Practices delivering both clinical and school-funded ABA need the two streams kept clearly apart to avoid duplicate-billing questions
  • Early intervention for the youngest children often runs on a separate funding track with its own eligibility
  • Coordinating with a school program protects the clinical case for medically necessary hours rather than undermining it

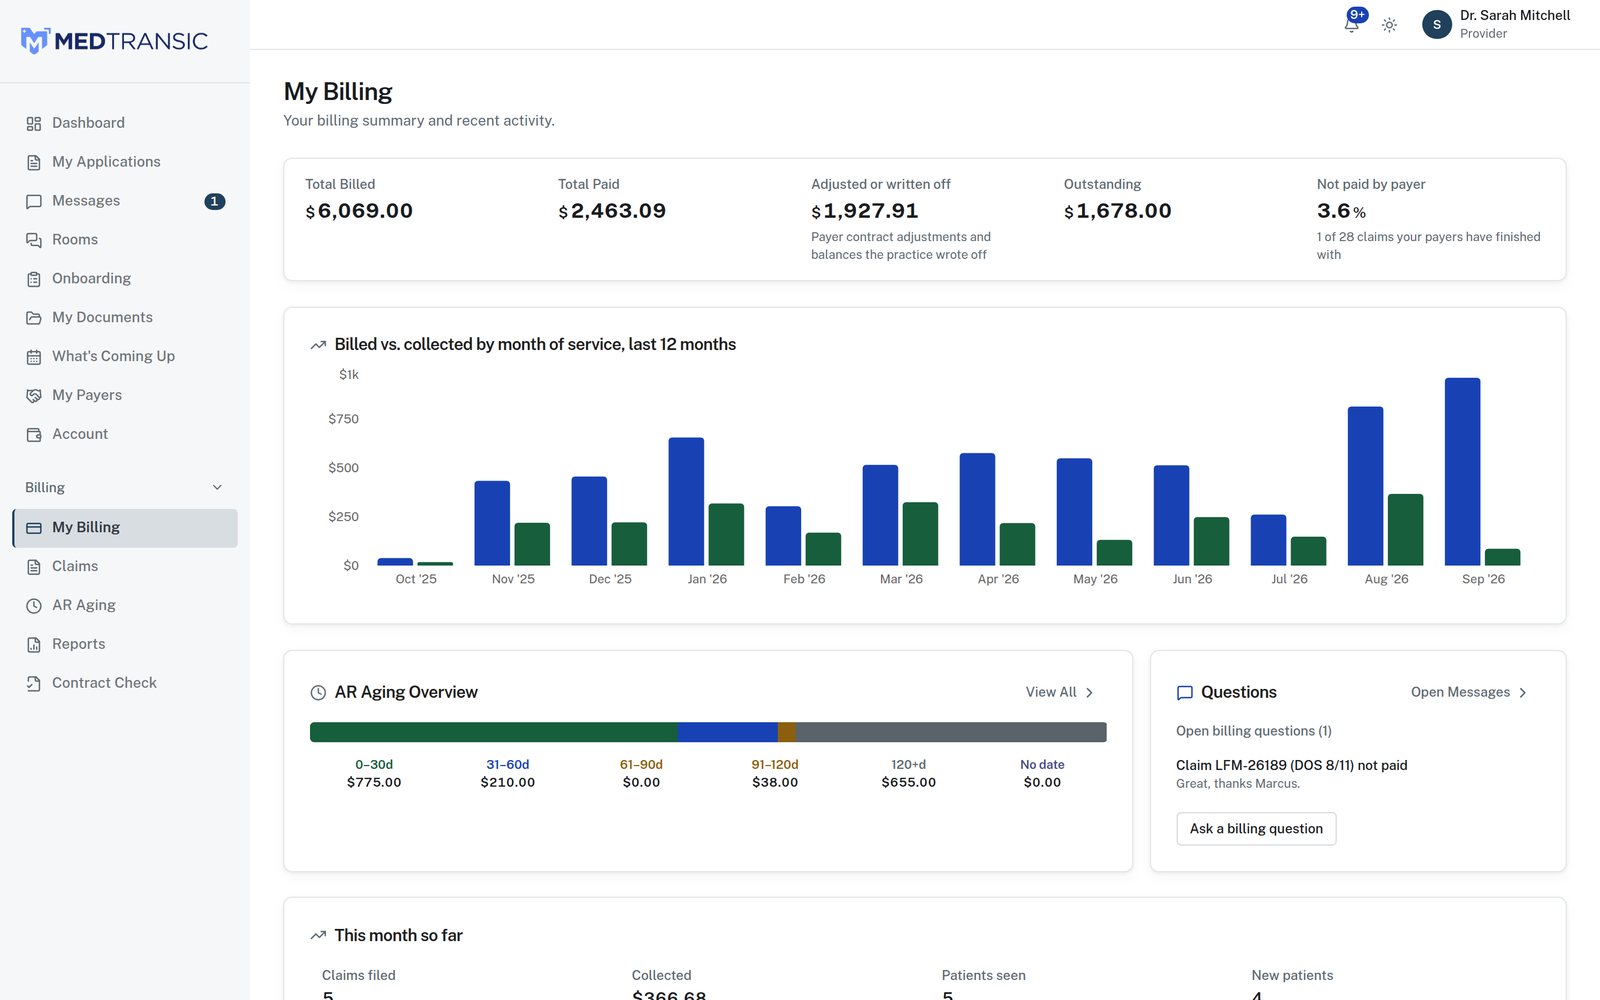
Your client portal, included

Your EHR shows what you billed. Your portal shows what we are doing about it.

Your EHR or practice management system runs your practice, but it does not show you our work. The Medtransic HIPAA Compliant Portal does: every claim and its current stage, the denials we are working, your A/R by age, each payer application and its in-network date, and the documents we still need from you. It is the same record our team works from, and it comes with every client account.

Did that claim get paid?
Every claim with its stage and amount, the denials we're working, and your receivables by age.
Where is my application with Aetna?
Each payer application shows its stage, its history, and the date you can start seeing that payer's patients.
What do you still need from me?
One list of the documents we're waiting on. Upload once, and it reaches every payer that asked for it.
See the client portal →
The billing screen in the Medtransic client portal: totals billed, paid, adjusted and outstanding, a twelve-month chart and A/R by age.
The billing screen. Shown with sample data. It works in any browser, on your desk or your phone. iPhone and Android apps are coming soon.

Frequently Asked Questions About ABA Therapy Billing

Expert answers to common questions about aba therapy billing, coding, insurance requirements, and revenue cycle management.

Still Have Questions?

Our team is ready to answer your specific questions and provide personalized guidance for your practice.

Book a Free Consultation

Find the Hours You Are Not Being Paid For

We will look at a sample of your authorizations and claims and show you where hours are being delivered outside an approval. No obligation, and no charge for the review.

Behavioral Health Billing TeamHIPAA Compliant & SecureDedicated Account Manager