
Medtransic Logo

Physical Therapy Billing Specialists

Physical Therapy Billing and Credentialing Services

Medtransic bills insurance and handles credentialing for physical therapy clinics. PT is one of our core practice types, alongside the other therapies and mental and behavioral health, our main specialty. We bill timed treatment as the right number of units, track plan-of-care signatures, visit limits and Medicare thresholds, and follow every claim until it is paid, inside WebPT or the system you already use. Billing is 4-8% of what we collect for you. Credentialing is $150 per application, per provider. There is no long-term contract.

Minutes are not unitsIllustrative sample
One sessionUnits
Therapeutic exercise23 min2
Manual therapy15 min1
Neuromuscular re-education8 min1
Unattended modality12 min, untimed1
58 minutes in the room5

Minutes are not units. The conversion is where therapy revenue is won or lost, and it depends on what the note records minute by minute.

Key takeaways

  • 01Physical therapy is billed by time, so small gaps in how minutes are documented quietly cost a clinic real revenue across a full schedule of patients.
  • 02Medicare's 2026 therapy threshold is $2,480 for physical therapy and speech-language pathology combined. It is not a cap: claims above it are paid when they carry the attestation that care is medically necessary, and denied without it (Centers for Medicare and Medicaid Services, Transmittal 13437, Change Request 14252).
  • 03Once a patient passes Medicare's annual therapy threshold, the practice keeps getting paid only when the record supports medical necessity and the claim attests to it.
  • 04Plan-of-care approvals, recertifications, and per-plan visit limits are where PT clinics lose the most to denials, and staying ahead of them is what keeps cash flowing.
  • 05Treatment units have to be calculated from the combined minutes of every timed service in the session, not service by service - the per-service shortcut quietly drops units your documentation already supports.
  • 06Monitoring patients between visits - home exercise adherence, pain levels, functional progress - is billable work under Medicare's remote therapeutic monitoring benefit, and many practices do this work without billing it.

How We Rebuild Physical Therapy Reimbursement

We handle the full physical therapy billing lifecycle - from charge capture through final payment - so your clinical team can focus entirely on patient care.

Step 01

Physical Therapy Billing Run by People Who Know It

You get billers who work PT every day and understand how timed treatment, evaluations, and therapy limits actually get paid - so more of what you deliver turns into collected revenue.

Every treatment minute captured as the units you actually earned / Evaluations billed at the level the visit truly supported / Fewer denials from billing and documentation gaps / More of each visit collected, the first time

Step 02

Medical Necessity & Documentation Support

We help make sure your notes carry the medical necessity payers look for, so continued care keeps getting paid instead of denied.

Progress notes reviewed against what payers require to keep paying / Guidance on showing why a therapist's skill is needed, whether care improves or maintains function / Preparation that holds up if a payer audits the chart / Fewer denials tied to documentation, fewer takebacks later

Step 03

Therapy Limit & Recertification Tracking

We watch each patient's cumulative therapy spending and plan-of-care dates so you never treat past an approval without knowing it.

Running tally of each patient's therapy spending toward the annual limit / Alerts before a plan of care needs recertification / Medical-necessity documentation lined up before the limit is reached / Care that continues past the limit still gets paid

Step 04

Authorization & Visit-Limit Management

We manage prior authorizations and per-plan visit caps so patients stay covered and you stop giving away visits for free.

Visit counts tracked against every patient's approved limit / New authorizations requested before the current one runs out / Plan-specific visit caps flagged before they're exceeded / Clear visibility into where each patient stands on coverage

Overlooked Revenue Leaks in Physical Therapy Billing

PT billing turns on timed units, plan-of-care rules and Medicare's therapy threshold, and each one can cost a clinic revenue.

1

You're Probably Getting Paid for Fewer Treatment Units Than You Actually Delivered

Most physical therapy treatment is paid by time, and the rules for how time converts into billable units are strict. When treatment minutes aren't recorded cleanly, the practice ends up billing fewer units than the therapist actually earned - every visit, across every patient on the schedule.

Impact: Lost revenue when delivered treatment minutes are underbilled

2

Past Medicare's Therapy Threshold, Visits Are Paid Only With the Right Attestation

Medicare sets an annual spending threshold on therapy. It is not a cap: past that point, care is still paid when the claim attests that it is medically necessary and the notes back that up. Without the attestation, Medicare denies the claims and the visits become unpaid work.

Impact: Denials past the annual therapy threshold when the medical-necessity attestation is missing

3

An Expired Plan of Care Turns Good Care Into Denied Claims

Medicare and most commercial plans require a signed plan of care that has to be recertified on a schedule. Let a certification lapse and every visit after it is billed against an expired authorization - clean treatment that gets denied purely on paperwork timing.

Impact: Denied visits when a plan of care lapses or is recertified late

4

Prior Authorization Runs Out Mid-Treatment and Nobody Catches It

Most payers only approve a set number of visits at a time. When a patient blows through that limit before a new authorization is in hand, the extra visits are delivered for free. Tracking visit counts against each patient's approval is what prevents it.

Impact: Free visits when authorization runs out mid-treatment

5

Evaluations Billed Like Routine Visits Are Worth Less Than the Work You Did

An initial evaluation, a re-evaluation, and a standard treatment session are each paid differently. When a detailed evaluation gets billed like an ordinary visit, the practice collects less than the clinical work actually justified.

Impact: Reduced reimbursement when evaluations are undervalued

6

When Two Services Happen in One Visit, Insurers Often Pay for Just One

When a therapist delivers more than one billable service in the same session, payers frequently bundle them and pay for only one unless the record shows they were genuinely separate. Get that wrong and the second service - real work you performed - simply disappears from the payment.

Impact: Lost payment when same-visit services get bundled

Physical Therapy Billing We Run

Specialty-tuned billing solutions tailored specifically for physical therapy practices and rehabilitation centers.

Evaluation & Re-evaluation Billing

Accurate billing for initial evaluations, re-evaluations, and discharge assessments so each is paid at the level the work supported.

Initial evaluations billed at the right complexity level / Re-evaluations captured, not folded into routine visits / Discharge documentation handled cleanly / Evaluation revenue you're currently leaving on the table

Treatment & Timed-Service Billing

Precise time-based billing for therapeutic exercise, manual therapy, and neuromuscular re-education across each session.

Treatment minutes converted into the correct billable units / Multiple same-visit services billed without lost payment / Timed minutes and total treatment time recorded to protect every unit / Fewer underbilled sessions across a full schedule

Modality Billing

Correct billing for physical-agent modalities, including which count toward timed treatment and which don't.

Supervised and hands-on modalities billed correctly / Untimed modalities kept out of your timed-minute totals / Documentation aligned to how each modality is paid / No lost revenue on the modalities you already provide

Plan of Care & Authorization Support

End-to-end handling of plan-of-care certification, recertification, and payer authorizations so coverage never lapses mid-treatment.

Plan-of-care certification and recertification tracked / Physician signatures chased before they hold up billing / Prior authorizations obtained and renewed on time / Visit limits monitored per patient, per plan

Inside Physical Therapy Billing

01

Physical Therapy Credentialing, Step by Step

A physical therapist has to be enrolled with each payer before the visits are paid in network. We handle it at $150 per application, per provider. In our experience it usually takes 60 to 90 days with each payer.

Medicare for PTs in private practice

  • Physical therapists in private practice enroll on Form CMS-855I.
  • A first private-practice enrollment triggers a site visit, ordered through PECOS.
  • Adding a location or moving one triggers another site visit.

Commercial plans

  1. 01Complete and attest your CAQH profile, then authorize each plan to read it.
  2. 02Apply to each plan, and ask whether its network is open to physical therapists in your area.
  3. 03Bill as in network only from the effective date on your contract.

PT credentialing is $150 per application, per provider

Usually 60 to 90 days with each payer, in our experience

Medicare private-practice PTs enroll on Form CMS-855I, with a site visit

Adding or moving a location means another Medicare site visit
02

Why PT Clinics Get Paid for Less Treatment Than They Deliver

Physical therapy is different from most specialties because so much of what a clinic bills is paid by time, not by a flat fee per visit. A therapist's minutes with a patient have to be translated into billable units, and the rules for that translation are unforgiving: fall a few minutes short and a unit disappears; document the minutes loosely and a payer can knock units off after the fact.

It rarely shows up as a dramatic denial - it shows up as a schedule full of visits that each billed one unit fewer than the therapist actually earned. Multiply that across every therapist and every day, and it becomes a large, invisible revenue leak in the practice.

How to stop the leak

The fix isn't working harder clinically; it's recording each session's timed minutes and total treatment time cleanly and converting them into units correctly, every time, so the billing finally matches the care that was delivered. Medicare asks for those two totals, not start and stop times, though some payers also want start and stop times.

Most PT treatment is paid by time, so how time is recorded directly decides how much you collect

A few undocumented minutes per visit becomes real money lost across a full schedule

Loose time notes let payers reduce your units after the claim is already paid

Clean minute counts are the difference between billing what you earned and billing less

03

Medicare's Therapy Threshold and Getting Paid Past It

Medicare sets an annual threshold for therapy spending on each patient, combining physical therapy and speech therapy under one amount: $2,480 in 2026. Reaching it doesn't mean the patient has to stop treatment, and it is not a cap.

Every visit past the threshold is paid when the claim carries the attestation that the care is still medically necessary and the record backs it up. If the attestation is missing, Medicare denies those claims, and the practice ends up treating for free.

Why the tracking is hard

Two things make this hard in practice. First, the threshold is cumulative across the whole year and across every provider the patient sees, so a clinic can't know where a patient stands just from its own visits. Second, the medical-necessity documentation has to be in place before the claims go out, not reconstructed after a denial.

Tracking each patient's cumulative therapy spending and preparing that justification ahead of time is what keeps care continuous and paid, instead of turning your most complex, highest-need patients into a source of write-offs.

Medicare's annual threshold combines physical and speech therapy for each patient: $2,480 in 2026

Care past the threshold still gets paid when the claim attests to medical necessity and the notes support it

The threshold is cumulative across the year and across every provider, so it has to be tracked centrally

A missing attestation means denials, so the documentation has to be ready before claims go out

04

Plan of Care, Recertification, and Authorization Timing

Before Medicare or most commercial plans will pay for physical therapy, there has to be a plan of care on file, certified by a physician, nurse practitioner, physician assistant or clinical nurse specialist, and Medicare requires it to be recertified at least every 90 days as treatment continues. This is one of the most common ways clean clinical work turns into denied claims: the therapy is appropriate, the notes are solid, but the certification lapsed or a recertification signature came in late, so every visit after that point is billed against an expired authorization.

Commercial visit limits

Commercial payers layer another timing problem on top - they typically approve only a limited number of visits at a time, and when a patient reaches that count before a new authorization is secured, the additional visits are delivered without coverage. None of this is a clinical failure; it's a tracking failure, and it's entirely preventable.

Watching plan-of-care dates, chasing physician signatures before they hold up billing, and requesting new authorizations before the current one runs out keeps coverage continuous so the practice gets paid for the care it's already committed to providing.

A signed plan of care is required before payers will pay, and it must be recertified on schedule

A lapsed certification or late signature turns good care into denied claims on timing alone

Commercial plans approve visits in limited batches that run out mid-treatment

Tracking dates and renewing authorizations early is what keeps coverage from lapsing

05

Unit Math Has to Be Done Across the Whole Session

There is a second layer to time-based billing that catches even experienced billers: under Medicare's method, units are calculated from the combined minutes of every timed service in the session, not from each service on its own. The correct method totals all timed minutes first, converts that total into the session's unit count, then distributes those units across the services delivered, starting with the one that took the most time.

A biller who calculates each service independently will often land on the same answer by coincidence, which is exactly why the error survives unnoticed. Change the time mix slightly and the shortcut drops a unit the documentation fully supported. Some commercial plans count each service separately, so we bill to each payer's method.

Untimed services and evaluations

There is a related trap on the other side: some services, such as unattended electrical stimulation, are paid once per visit no matter how long they run. Hot and cold packs are not paid separately by Medicare at all. Neither belongs in the timed total.

Letting those minutes in inflates the unit count, which is a compliance problem rather than extra revenue. Evaluations sit in this untimed category too, paid per encounter at the complexity level the notes support.

Units come from the session's combined timed minutes, then get distributed across services

Per-service math often matches by coincidence, so the error hides until the time mix changes

Untimed services are paid once per visit and their minutes never enter the timed total; hot and cold packs are not paid separately by Medicare

Evaluations are untimed and paid per encounter at the complexity the documentation supports

06

Between-Visit Monitoring Is Work You Can Bill For

Many PT practices already keep tabs on patients between appointments: checking whether the home exercise program is being followed, tracking pain levels, watching functional progress ahead of the next visit. Under Medicare's remote therapeutic monitoring benefit, that work is billable when it is set up and documented properly.

The benefit covers the initial setup and patient education, the supply of the monitoring device or software, and the time the therapist spends each month reviewing the data and communicating with the patient about it, provided the interactive time meets Medicare's monthly minimum.

Why it goes unbilled

When a practice collects none of this, the reason is usually simple: its billing operation either does not know the benefit exists or has no workflow to identify eligible patients and capture the monthly requirements. For clinics managing chronic conditions or long post-surgical recoveries, that is recurring revenue being forfeited on work the therapists are already doing informally. Building eligibility screening and monthly documentation into the routine turns an unpaid habit into a paid service line.

Medicare pays for remote monitoring of home exercise adherence, pain, and functional progress

Setup, device supply, and monthly management time are each separately billable

Monthly management requires a documented minimum of interactive time with the patient

Many practices do this work informally without billing it

07

What a Well-Run PT Billing Operation Should Deliver

Practice owners rarely know whether their billing is performing because nobody gives them numbers to hold it against. Ask any billing company for four numbers in writing, and review them monthly:

  • Clean-claim rate: the share of claims accepted on first submission
  • PT denial rate: for your PT claims, not a blended figure across specialties
  • Days in accounts receivable: how long, on average, a claim takes to be paid
  • Net collection rate: what was collected of what could be collected, after contractual adjustments

Two non-negotiables

Two standards should be treated as absolute rather than aspirational. First, no Medicare claim should ever go out missing the required plan-of-care designation, because that omission is an automatic denial. Second, once a patient crosses Medicare's annual therapy threshold, the medical-necessity attestation must appear on every subsequent claim without exception.

Put these measures in writing before an engagement starts and review them monthly. A billing partner that resists being measured against specific numbers is answering the question for you.

Ask for the clean-claim rate, PT denial rate, days in accounts receivable and net collection rate in writing

Ask for a PT-specific denial rate, not a blended figure across every specialty a biller handles

The plan-of-care designation and the post-threshold necessity attestation allow zero misses

Put these measures in writing before the engagement and review them every month

Physical Therapy Payer Rules

Each payer has its own rules for physical therapy billing, and we bill to each one.

Medicare

Medicare Part B

  • Medicare keeps paying past its annual therapy threshold ($2,480 in 2026) when the claim attests that continued care is medically necessary - the documentation behind that has to be ready before claims go out
  • A certified plan of care must be on file and recertified at least every 90 days; late signatures put payment at risk
  • When a physical therapist assistant provides more than 10 percent of a service, Medicare pays it at 85 percent of the therapist rate, and the claim must identify assistant-delivered services or it can process at the wrong rate or draw an audit
  • Above a second, higher spending threshold ($3,000), Medicare's regional contractors can pull claims for targeted manual review - documentation there needs to show why a therapist's skill is needed and set specific treatment goals
  • Medicare pays physical therapists for telehealth through December 31, 2027, unless Congress extends it

Medicaid

Medicaid (State Plans)

  • Coverage, visit limits, and approval requirements vary sharply from state to state, so what pays in one state may be denied in another
  • Many state programs require approval for therapy beyond a handful of visits, and treating past that without it means unpaid care
  • Managed Medicaid plans often route billing through their own portals with their own rules - verifying which applies avoids rejected claims
  • Children's coverage generally pays for medically necessary therapy without the same visit caps, which protects that revenue when documented well

Commercial

Commercial & Managed Care

  • Most commercial plans require approval after the initial evaluation, so care started before it's secured is care at risk of not being paid
  • Many plans cap therapy at a set number of visits per year - tracking each patient's count prevents giving away visits for free
  • A patient's plan and benefits can change at the start of the plan year, so we re-verify coverage when a new plan year starts
  • Some plans require documented outcome measures to keep authorizing care, so building those into the notes protects continued payment

All payers

Workers' Compensation

  • In most states, workers' comp pays on a state fee schedule rather than standard rates, so the practice needs to bill to the right schedule to collect fully
  • Many claims require separate approval or a progress report for each stretch of visits, and missing one stalls payment
  • Return-to-work goals usually have to be documented alongside functional progress or the payer questions continued care
  • Claims tie to a specific injury and date, so getting that detail right up front avoids denials and delays

Your client portal, included

Your EHR shows what you billed. Your portal shows what we are doing about it.

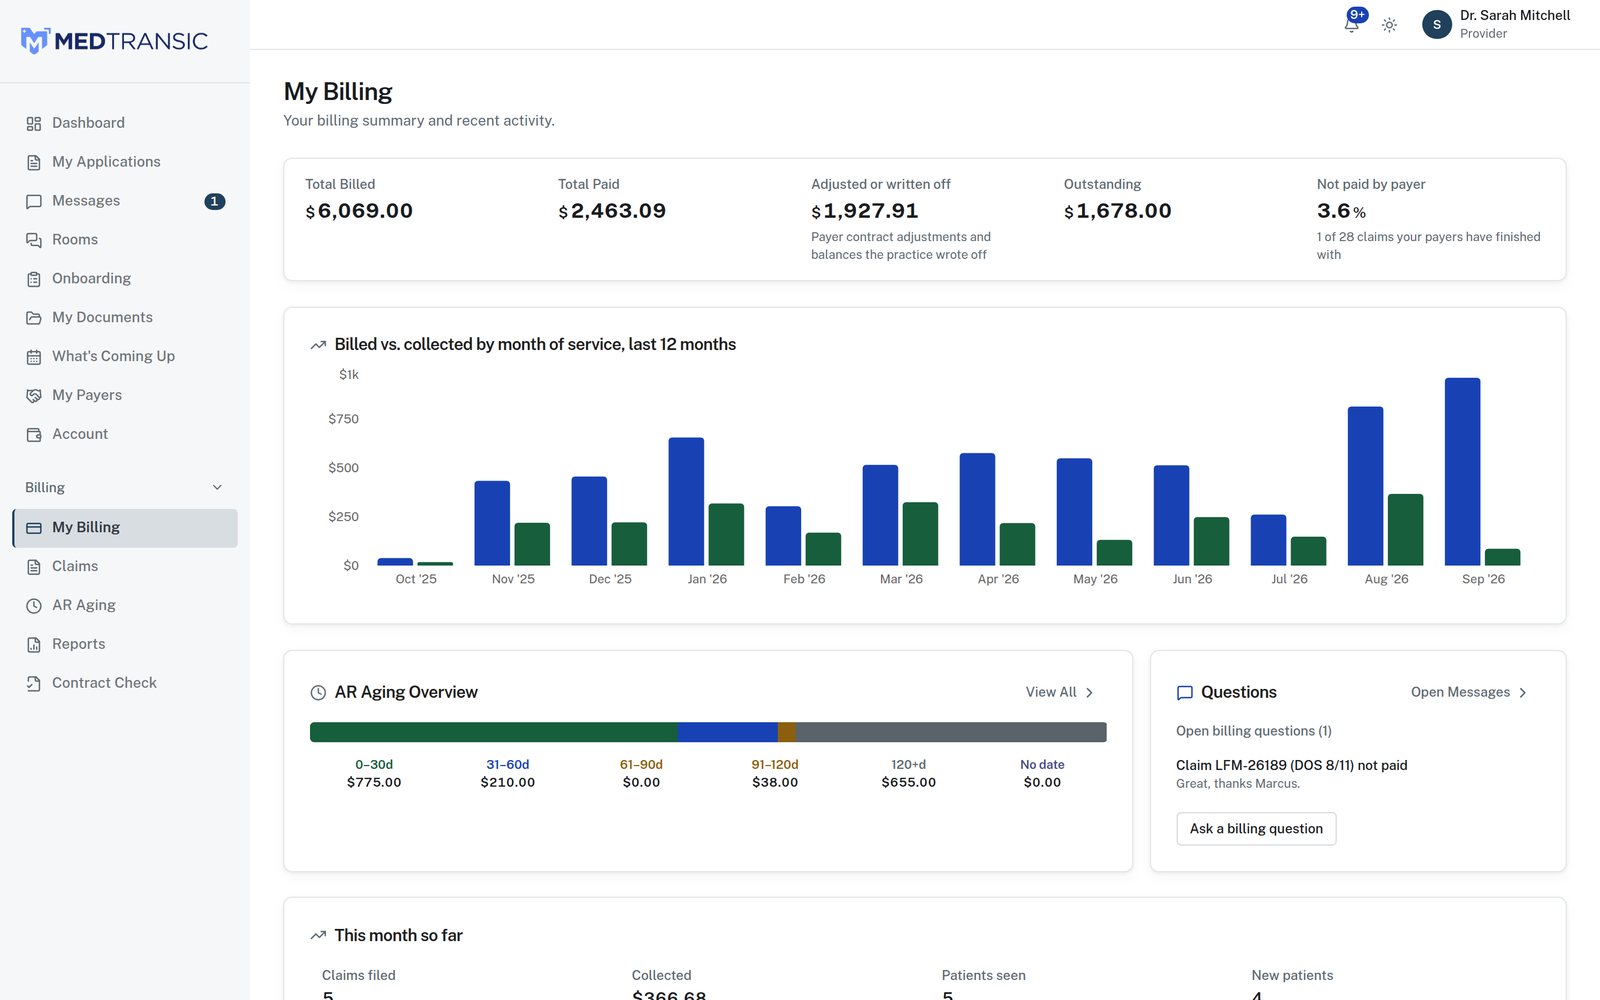
Your EHR or practice management system runs your practice, but it does not show you our work. The Medtransic HIPAA Compliant Portal does: every claim and its current stage, the denials we are working, your A/R by age, each payer application and its in-network date, and the documents we still need from you. It is the same record our team works from, and it comes with every client account.

Did that claim get paid?
Every claim with its stage and amount, the denials we're working, and your receivables by age.
Where is my application with Aetna?
Each payer application shows its stage, its history, and the date you can start seeing that payer's patients.
What do you still need from me?
One list of the documents we're waiting on. Upload once, and it reaches every payer that asked for it.
See the client portal →
The billing screen in the Medtransic client portal: totals billed, paid, adjusted and outstanding, a twelve-month chart and A/R by age.
The billing screen. Shown with sample data. It works in any browser, on your desk or your phone. iPhone and Android apps are coming soon.

Frequently Asked Questions About Physical Therapy Billing

Expert answers to common questions about physical therapy billing, coding, insurance requirements, and revenue cycle management.

Still Have Questions?

Our team is ready to answer your specific questions and provide personalized guidance for your practice.

Book a Free Consultation

Take Control of Physical Therapy Reimbursement

Get a no-obligation look at how your physical therapy billing stacks up. Our specialists will review your top denial reasons and show you a concrete plan to close the revenue gap.

PT Billing SpecialistsHIPAA Compliant & SecureDedicated Account Manager