
Community mental health centers and CCBHCs
Community Mental Health Center and CCBHC Billing
Medtransic bills insurance for community mental health centers and certified community behavioral health clinics (CCBHCs). We send and follow up on Medicaid, Medicare and commercial claims, including partial hospitalization under the center, and we credential and enroll the center and each clinician who bills. We work inside your existing system, such as Qualifacts. Billing is 4-8% of what we collect for you. Credentialing is $150 per application, per provider, and there is no long-term contract.
- Billing
- 4-8%
- of what we collect for you
- Credentialing
- $150
- per application, per provider
- Contract
- None
- no long-term contract
- Software
- Qualifacts
- or the system you already use
The nine required CCBHC services
Illustrative- 01
Crisis services
Including 24-hour mobile crisis teams
- 02
Screening, assessment and diagnosis
- 03
Patient-centered treatment planning
- 04
Outpatient mental health and substance use services
- 05
Primary care screening and monitoring
- 06
Targeted case management
- 07
Psychiatric rehabilitation
- 08
Peer support, counselor services and family supports
- 09
Intensive community-based care for service members and veterans
Where a community center's revenue slips
A center bills under several payment systems at once, each with its own rules.
- A therapist's claim for a program service
- When a Medicare center runs partial hospitalization or intensive outpatient care, Medicare does not pay its social workers, counselors or family therapists under their own benefit for that work. The center bills.
- Program days without a current certification
- A physician must certify the need for at least 20 hours a week of partial hospitalization, and recertify at least every 30 days. Days after a lapsed recertification have nothing behind them.
- A CCBHC rate built on weak cost reports
- Your state rebases CCBHC rates on cost reports. If claims data and finance reports do not match, the next rate starts from the wrong numbers.
- Peer support that misses the payer's terms
- Medicaid peer support needs supervision, a plan of care and state-defined training. Without them, a peer service falls short of the federal minimum.
Our part, and your center's part
Medtransic runs
- Medicaid, Medicare and commercial eligibility checks before services start
- Center claims, including partial hospitalization, and claims for clinicians under their own numbers
- Payment posting, with each payment checked against the payer's rate
- Denials and appeals, worked back to a cause so they stop repeating
- A/R follow-up before filing and appeal deadlines pass
- Credentialing and enrollment for the center and each clinician who bills
Your practice keeps
- Clinical care, treatment plans, certifications and notes
- Medicaid and CCBHC cost reports, which stay with your finance team or accountant
- Quality and outcome reporting to your state
- Your EHR, your staff and your state certification
What CCBHC status asks of a center, and how it pays
Federal rules for the CCBHC Medicaid demonstration and for Medicare community mental health centers, current as of October 2026. States add their own rules on top.
The nine services a CCBHC must offer
The statute lists crisis services, including 24-hour mobile crisis teams; screening, assessment and diagnosis; patient-centered treatment planning; outpatient mental health and substance use services; primary care screening and monitoring; targeted case management; psychiatric rehabilitation; peer support, counselor services and family supports; and intensive community-based care for service members and veterans. A clinic may provide some of these through formal relationships with other providers.
Open to everyone who walks in
A CCBHC must use a sliding fee scale and may not refuse or limit services because of ability to pay or where a patient lives. It must also report encounter, clinical outcome and quality data.
Four ways a state can pay
Demonstration states choose one of four cost-based, clinic-specific methods: a daily rate, a monthly rate, or either one with separate rates for special crisis services. Quality bonus payments are optional under the daily methods and required under the monthly ones.
One daily payment per person
Under the daily method, a clinic gets at most one payment per person per day. The daily rate is total allowable annual costs divided by annual daily visits.
Cost reports and rebasing
Rates are updated each year by the Medicare Economic Index or by rebasing on cost reports. States must rebase for demonstration year 3 using year 2 cost reports, and at least every 3 years after that.
Which states are in the demonstration
Thirty states have been selected in all: 8 original states, 2 under the CARES Act and two rounds of 10 under the Bipartisan Safer Communities Act. The second round, Alaska, Colorado, Hawaii, Louisiana, Maryland, Mississippi, Montana, North Dakota, Washington and West Virginia, starts between July 1, 2026 and July 1, 2027.
Medicare's 40% rule
A Medicare community mental health center must give at least 40% of its services to people who are not Medicare beneficiaries. It must also hold state licensing or certification and provide outpatient services and 24-hour emergency care.
How Medicare pays partial hospitalization
Medicare pays a center's partial hospitalization as a daily rate, with one rate for days with three services and another for four or more. For 2026, CMS bases center costs on 40% of hospital-based partial hospitalization costs.
Governance and telehealth
A Medicare center needs a governing body of at least two people, one a mental health clinician, and an administrator who is its own employee. A center can also be a Medicare telehealth originating site.
Enrolling the center and credentialing its clinicians
A center enrolls as an organization, then for each clinician who bills under their own number.
The center's own enrollment
We file the center's Medicare enrollment in PECOS, separately from your state Medicaid enrollment and your commercial contracts.
Clinicians who bill outside the program
Therapists, psychiatrists and nurse practitioners who bill under their own numbers each get applications, with CAQH profiles kept complete and attested.
Peer specialists under state rules
We collect each peer specialist's state training and certification records, so what your Medicaid plans expect is on hand.
Effective dates in your portal
Every application, its stage and the documents we still need sit in your client portal.
Payer notes for community centers
Medicaid and Medicare each set their own terms for CCBHC services, program days and peer support.
| Payer | Service | The rule |
|---|---|---|
| Medicaid | CCBHC services | Paid at the clinic-specific rate your state set, not a fee per service. We bill the way your state built that rate. |
| Medicare | Partial hospitalization and intensive outpatient care | The center bills, not its social workers, counselors or family therapists. Partial hospitalization is paid as a daily rate. |
| Medicaid | Peer support | Supervision by a competent mental health professional, services tied to an individualized plan of care, and state-defined training and certification (CMS, 2007). |
| Medicare | Peer support | Only as principal illness navigation services delivered by peer support specialists under general supervision. |
Your client portal, included
Your EHR shows what you billed. Your portal shows what we are doing about it.
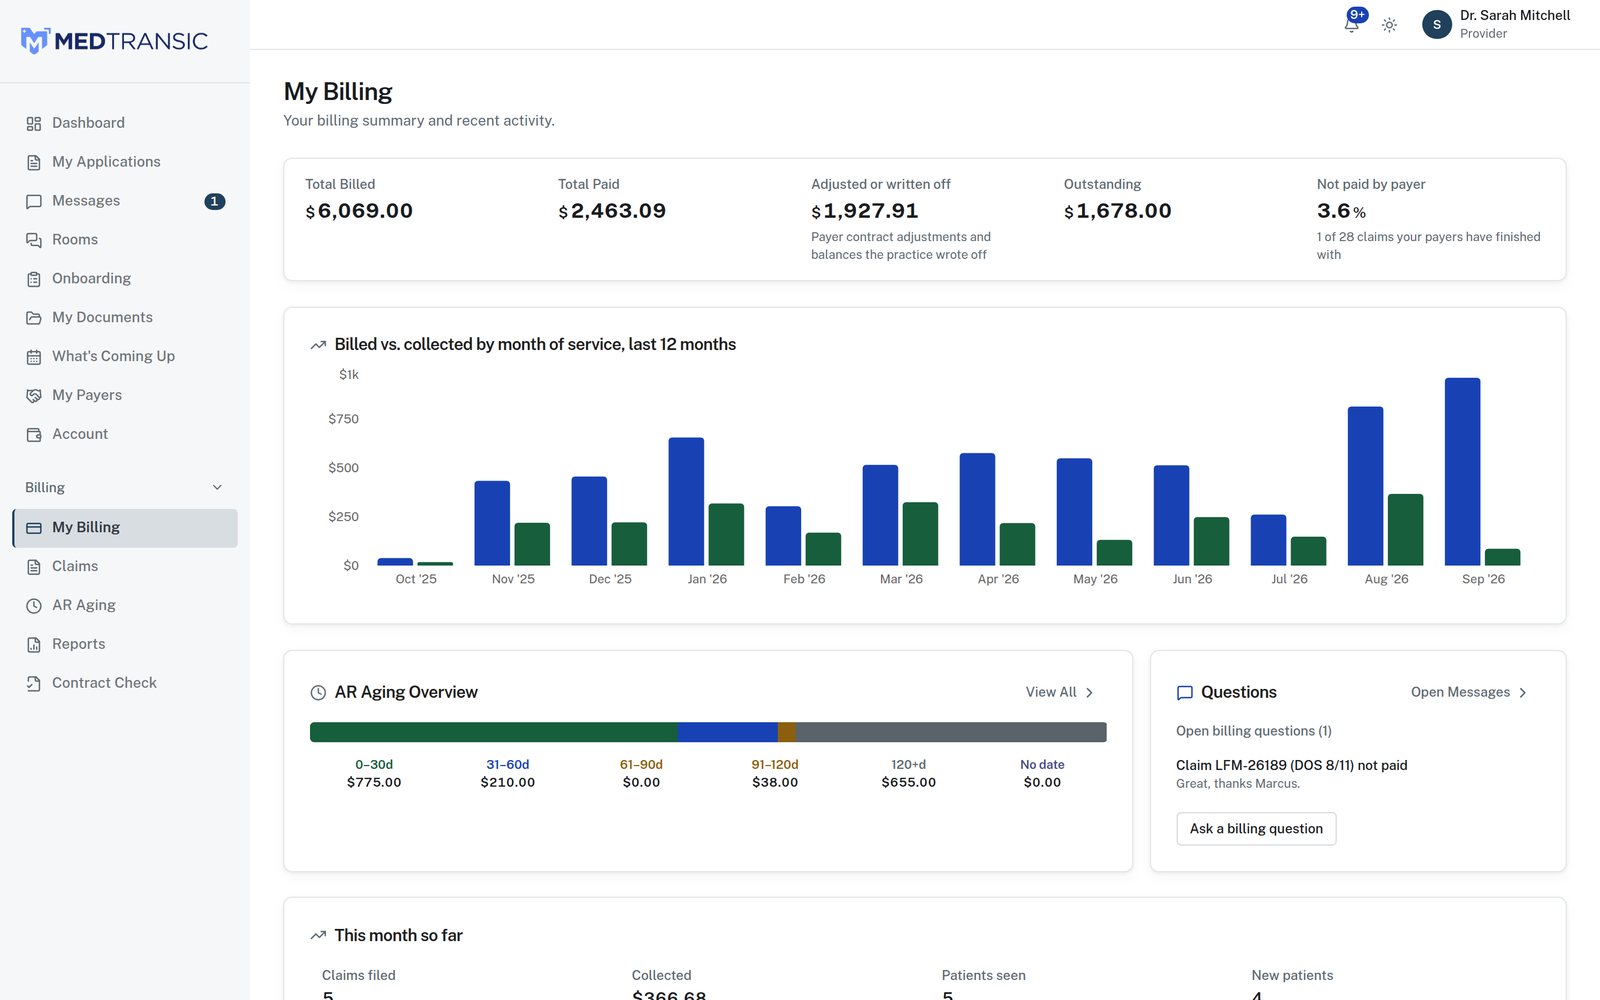
Your EHR or practice management system runs your practice, but it does not show you our work. The Medtransic HIPAA Compliant Portal does: every claim and its current stage, the denials we are working, your A/R by age, each payer application and its in-network date, and the documents we still need from you. It is the same record our team works from, and it comes with every client account.
- Did that claim get paid?
- Every claim with its stage and amount, the denials we're working, and your receivables by age.
- Where is my application with Aetna?
- Each payer application shows its stage, its history, and the date you can start seeing that payer's patients.
- What do you still need from me?
- One list of the documents we're waiting on. Upload once, and it reaches every payer that asked for it.
When we are not the right fit
- If you run a large multi-site agency with its own billing department that keeps claims clean and paid, you may not need us. We fit centers whose billing team is small, stretched or about to change.
- We do not prepare Medicaid or CCBHC cost reports. That work stays with your finance team or your accountant.
Questions community mental health centers ask us
How much does billing for a community mental health center cost?
Billing is 4-8% of what we collect for you, with no long-term contract. Credentialing is $150 per application, per provider. The consultation before you sign is free.
Do you prepare our CCBHC cost report?
No. Cost reports stay with your finance team or accountant. We bill, credential and enroll the center and its clinicians.
Can our social workers bill Medicare for partial hospitalization days?
No. When a center provides partial hospitalization or intensive outpatient care, Medicare does not pay social workers, counselors or family therapists under their own benefit for it. The center bills those services.
What is the 40% rule?
A Medicare community mental health center must give at least 40% of its services to people who are not Medicare beneficiaries. It is one of the conditions for being a Medicare center at all.
How often are CCBHC rates rebased?
States update rates each year by the Medicare Economic Index or by rebasing on cost reports. They must rebase for demonstration year 3 using year 2 cost reports, then at least every 3 years.
Which systems do you work in?
We work inside your existing system, including Qualifacts, SimplePractice, TherapyNotes and CentralReach, so your center does not switch software to work with us.
Keep reading
- Behavioral health groups and clinics →
- Substance use treatment billing →
- Credentialing for therapists and behavioral health →
- Payer enrollment →
- Qualifacts billing →
- Mental health IOP and PHP billing →
- Psychiatry billing →
- Child and adolescent mental health billing →
- Counselor credentialing (LCSW, LPC, LMFT) →
- Pricing →
+ − Sources: 10 checked 2026-10-04
- Protecting Access to Medicare Act of 2014, section 223 (Public Law 113-93), CCBHC criteria, checked 2026-10-04
- Medicaid.gov, Certified Community Behavioral Health Clinic (CCBHC) Demonstration, checked 2026-10-04
- Medicaid.gov, CCBHC Prospective Payment System and Quality Bonus Payments, checked 2026-10-04
- CMS, Section 223 CCBHC Demonstration PPS Guidance (updated February 2024), checked 2026-10-04
- 42 CFR 410.2, definition of a community mental health center, checked 2026-10-04
- 42 CFR 485.918, CMHC conditions of participation: organization, governance and administration, checked 2026-10-04
- CMS, Medicare & Mental Health Coverage (MLN1986542, March 2026), checked 2026-10-04
- CMS, Telehealth & Remote Patient Monitoring (MLN901705, December 2025), checked 2026-10-04
- CMS, CY 2026 OPPS and ASC final rule fact sheet, checked 2026-10-04
- CMS, State Medicaid Director Letter on peer support services (SMDL 07-011, August 15, 2007), checked 2026-10-04
Book a free consultation
We look at a sample of your actual claims and show you, line by line, where money is going uncollected. No commitment follows it.